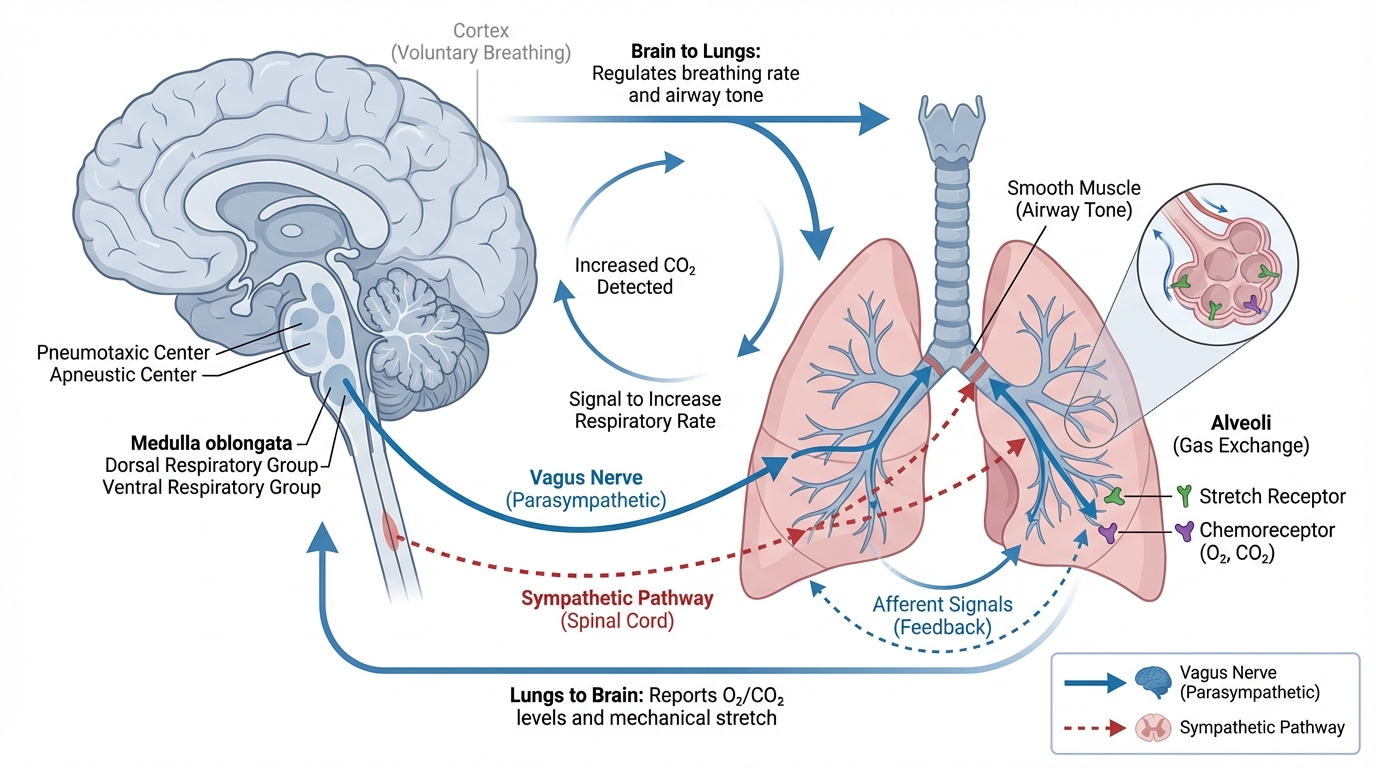
Ever felt like you’re fighting your own ventilator? While traditional fixed-pressure bilevel ventilation (BiPAP) has long been a staple in acute and chronic respiratory care, its static settings struggle to keep up when a patient’s respiratory mechanics shift during sleep, posture changes, or diaphragmatic exhaustion.
Enter Average Volume Assured Pressure Support (AVAPS)—an intelligent, closed-loop modality engineered to dynamically titrate inspiratory pressure in real time to guarantee a stable tidal volume[cite: 1, 2]. By seamlessly adapting pressure support to meet fluctuating physiological demands, AVAPS significantly unloads the mechanical work of breathing, optimizes nocturnal alveolar ventilation and carbon dioxide clearance, and slashes intubation rates in acute hypercapnic failure.
Whether managing obesity hypoventilation, neuromuscular weakness, or complex COPD exacerbations, AVAPS bridges the gap between patient comfort and volume security to deliver truly individualized ventilatory support.
Tune into the latest episode of The RT Edge Podcast, “Volume-Assured Pressure Support vs. Fixed Pressure NIV: Which Wins the COPD Battle?”, where we break down bedside waveforms, titration protocols, and the clinical evidence deciding the future of respiratory care.
Average Volume Assured Pressure Support (AVAPS) operates as a closed-loop pressure-adaptation servo-controller. Unlike standard bilevel positive airway pressure (BiPAP S/T) with fixed pressure support (ΔPS), AVAPS automatically recalculates a rolling moving average of expired tidal volume (Vte) over multiple breaths. If delivered volume drops due to changes in patient compliance, body posture, or muscle fatigue, the algorithm incrementally raises IPAP toward a clinician-set ceiling (IPAPmax). Conversely, as effort recovers, pressure is down-titrated to IPAPmin.
AVAPS Dynamic Closed-Loop WorkflowServo Logic
Step 1: Measurement
Expiratory Flow Sensor
Calculates rolling moving average of Vte over 1–2 minutes
Step 2: Comparison
Target VT vs Measured Vte
Detects volume deficits or surpluses against preset target
Step 3: Titration
IPAP Modulation
Adjusts IPAP by 0.5 to 5.0 cmH₂O/min within limits
Initial IPAP Calculation Formula:
IPAPinitial = ( Target VT / 60 mL/cmH₂O ) + EPAP
Establishes initial delivery assuming nominal compliance of 60 mL/cmH₂O before rolling average stabilizes.
Comparing control variables and flexibility across modern advanced non-invasive ventilation modes.
Key Context: AVAPS uniquely bridges fixed-pressure BiPAP S/T and complex alveolar ventilation modes (iVAPS). It guarantees expired volume safety without requiring accurate estimation of anatomical dead space (VD).
Arterial carbon dioxide tension (PaCO₂) is inversely proportional to alveolar minute ventilation (V̇A = RR × [VT - VD]). In shallow, rapid breathing, an increased fraction of tidal volume is wasted on anatomical dead space (VD), leading to profound hypercapnia. AVAPS counteracts nocturnal hypoventilation and diaphragmatic exhaustion by maintaining delivered tidal volumes above dead space during sleep stage transitions, preventing respiratory muscle failure.
Effective Alveolar Ventilation (V̇A) vs Dead Space Waste
How increasing tidal volume under AVAPS restores clearance of carbon dioxide compared to shallow rapid breathing.
Takeaway: At a constant minute ventilation of 6.0 L/min, shallow breathing (VT = 250 mL, RR = 24) wastes 60% of ventilation on dead space (VD = 150 mL). Restoring VT to 600 mL with AVAPS reduces dead space waste to 25%, boosting effective alveolar ventilation from 2.4 to 4.5 L/min.
AVAPS is optimal for disorders characterized by variable thoracic compliance, respiratory muscle weakness, or sleep-dependent hypoventilation. Understanding phenotype-specific pressure and volume targets is critical for successful clinical deployment.
Prescribed Target Volume (VT) and EPAP Range by Clinical Phenotype
4
Algorithmic Latency, Air Leaks & Clinical Contraindications
While AVAPS provides outstanding volume stability in subacute and chronic care, its deliberate rate-of-change titration mechanism (1.0 to 2.5 cmH₂O/min) introduces algorithmic latency. In rapidly crashing patients or high-leak environments, AVAPS can lead to treatment failure if misapplied.
⏱️ Algorithmic Latency Hazard
In fulminant decompensation (pH < 7.15, tachypnea > 38 bpm), diaphragmatic exhaustion occurs in 1 to 3 minutes. AVAPS takes several minutes to ramp pressure support from IPAPmin to IPAPmax.
Patient Exhaustion Rate1–3 Minutes
AVAPS Pressure Ramping4–8 Minutes
Rule of Thumb: Crashing patients require immediate fixed high-intensity BiPAP (ΔPS ≥ 15 cmH₂O) or endotracheal intubation.
🔄 Unintentional Leak Feedback Loop
When mask leak exceeds 30 L/min, the flow sensor underestimates exhaled volume (Vte). AVAPS misinterprets leak as hypoventilation, sparking a dangerous positive feedback cycle.
1
Mask seal breaks (>30 L/min leak)
2
Sensor underestimates expired Vte
3
Algorithm drives IPAP to IPAPmax
4
High pressure blows mask seal further
🚫 Absolute Contraindications
•Cardiorespiratory Arrest / Severe Bradypnea: Requires immediate invasive airway control.
•Severe Hemodynamic Instability: Unresuscitated shock or life-threatening ventricular arrhythmias.
•Inability to Protect Airway: Impaired cough, massive secretions, or severe bulbar dysfunction.
•Facial Trauma / Burns: Anatomy preventing mask seal or risking tissue necrosis.
•Active GI Bleeding / Vomiting: Extreme risk of aspiration under positive pressure.
Mastering AVAPS requires configuring appropriate pressure windows (IPAPmax - IPAPmin ≥ 6--10 cmH₂O) and performing bedside waveform analysis to eliminate dyssynchrony phenotypes.
Bedside Dyssynchrony & Waveform Solver
Click a dyssynchrony phenotype to inspect mechanics and RT solutions.
RT Troubleshooting
Low VT Alarm Setup: Set at 90% of target VT. If triggered for >60s, it indicates IPAPmax ceiling is restricting required pressure delivery.
ABG Surveillance Timeline: Draw baseline ABG, then repeat at 1–2 hours post-initiation. Monitor PtcCO₂ during nocturnal titrations.
Dyssynchrony Phenotype Frequency in AVAPS
Relative frequency of dyssynchrony events during non-invasive volume assurance therapy.
Clinical Focus: Ineffective triggering and pressure clamping account for over 55% of dyssynchrony challenges. Both are usually resolved by adjusting EPAP (to counter Auto-PEEP) or resetting IPAPmax headroom.
function calculateIBW() {
const sex = document.getElementById('calcSex').value;
const height = parseFloat(document.getElementById('calcHeight').value);
const pathology = document.getElementById('calcPathology').value;
if (isNaN(height) || height < 36) return;
let ibw = 50;
if (sex === 'male') {
ibw = 50 + 2.3 * (height - 60);
} else {
ibw = 45.5 + 2.3 * (height - 60);
}
if (ibw < 10) ibw = 10;
let vtLow = 0;
let vtHigh = 0;
if (pathology === 'restrictive') {
vtLow = ibw * 8;
vtHigh = ibw * 10;
} else {
vtLow = ibw * 6;
vtHigh = ibw * 8;
}
let ipapMax = pathology === 'restrictive' ? 28 : 25;
document.getElementById('resIBW').innerText = ibw.toFixed(1) + ' kg';
document.getElementById('resVtLow').innerText = Math.round(vtLow) + ' mL';
document.getElementById('resVtHigh').innerText = Math.round(vtHigh) + ' mL';
document.getElementById('resIpapMax').innerText = ipapMax + ' cmH₂O';
}
document.getElementById('calcSex').addEventListener('change', calculateIBW);
document.getElementById('calcHeight').addEventListener('input', calculateIBW);
document.getElementById('calcPathology').addEventListener('change', calculateIBW);
calculateIBW();
const dysData = {
ineffective: {
title: "Ineffective Triggering (Wasted Effort)",
mechanism: "Uncompensated intrinsic PEEP (Auto-PEEP) in COPD; trigger threshold exceeds patient effort capability.",
waveform: "Negative pressure deflection on pressure-time curve without subsequent ventilator breath delivery.",
solution: "Increase EPAP to offset Auto-PEEP; reduce target V_T to prolong expiratory time (T_E); increase flow trigger sensitivity."
},
autotrigger: {
title: "Auto-Triggering",
mechanism: "Interface leaks or cardiogenic flow oscillations causing false triggers when no patient effort exists.",
waveform: "Unusually high ventilator delivery rate with irregular baseline flow and absence of muscular deflection.",
solution: "Re-fit mask cushion seal; reduce trigger sensitivity threshold; fine-tune Auto-Trak leak compensation parameters."
},
delayed: {
title: "Delayed Cycling (Prolonged Insufflation)",
mechanism: "Unintentional air leak prevents circuit flow from decaying to the inspiratory cycling threshold percentage.",
waveform: "Inspiratory pressure plateau persists into neural expiration; terminal upward pressure spike on scalar.",
solution: "Set maximum inspiratory time limit (T_I max: 1.2–1.4s); fix interface mask leaks; increase cycling flow percentage."
},
premature: {
title: "Premature Cycling (Short Cycling)",
mechanism: "Rapid flow decay in stiff or non-compliant lungs truncates ventilator delivery before neural inspiration ends.",
waveform: "Abrupt termination of flow followed by immediate secondary re-triggering (double triggering phenomenon).",
solution: "Increase minimum inspiratory time (T_I min ≥ 0.8s); soften rise time setting to round pressurization curve."
},
clamping: {
title: "Pressure Clamping (Pegged at IPAP Max)",
mechanism: "Severe mask leak or elevated thoracic impedance causes calculated V_te to persistently fall below target V_T.",
waveform: "IPAP delivered at prescribed IPAP_max limit on every single breath; low V_T alarm continuously active.",
solution: "Inspect and seal mask leaks; clear airway secretions; if impedance is real, safely expand IPAP_max ceiling window."
}
};
function showDyssynchrony(key) {
const item = dysData[key];
const container = document.getElementById('dysDisplay');
container.innerHTML = `
Welcome to Master Respiratory, a blog focused on the fascinating world of respiratory care. Our blog is dedicated to helping healthcare professionals, students of any profession, and anyone curious about the lungs alike understand the complexities of the respiratory system and its treatments, concepts, tools, and therapies.
Welcome to Master Respiratory, a blog focused on the fascinating world of respiratory care. Our blog is dedicated to helping healthcare professionals, students of any profession, and anyone curious about the lungs alike understand the complexities of the respiratory system and its treatments, concepts, tools, and therapies.
Master Respiratory was created to become that new resource for RT’s and everyone else who wants to learn a bit more about Respiratory care. A post that can discuss a previously learn topics, or a introduction to a innovation new vent mode, everything and anything is posted to help us master our craft!!