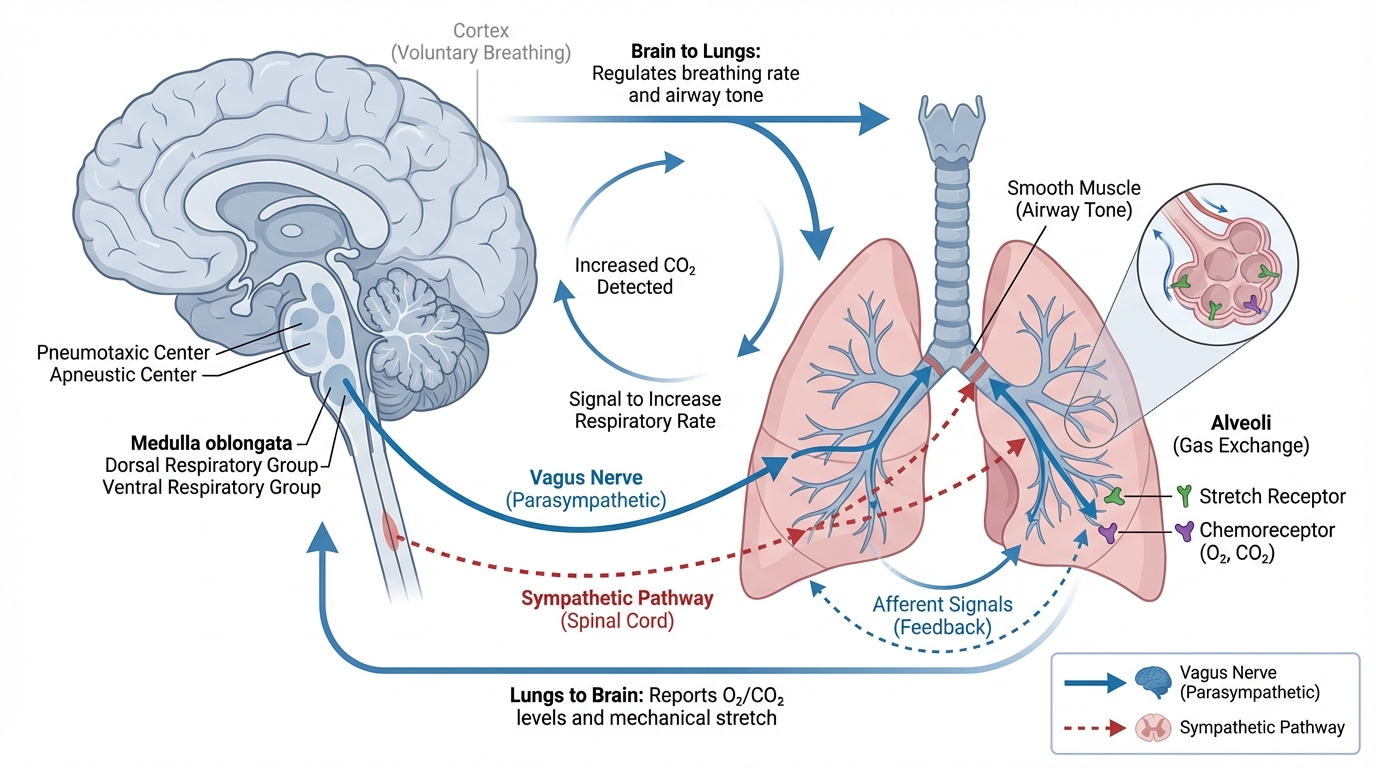
Have you ever wondered how we went from massive, clunky iron lungs to the sophisticated, computer-driven ventilators we use in the neuro-ICU today? The journey isn’t just a story of better technology; it’s a dramatic tale of shifting philosophies, hard-learned lessons, and a deeper understanding of how the brain and lungs are connected. To truly master modern neuro-ventilation, we have to look back at the pivotal moments that shaped where we are now.
This trip through history will show you why we do what we do at the bedside. We’ll explore the desperate innovation of the polio era, the rise and fall of aggressive hyperventilation, and the paradigm shift that led to today’s brain-protective strategies. Understanding this evolution will give you a powerful “why” behind the settings you choose and the protocols you follow.
The Birth of an Idea: The 1952 Polio Epidemic
Our story begins not with a head injury, but with a neurological crisis that paralyzed the world: the 1952 poliomyelitis epidemic in Copenhagen. Hospitals were overwhelmed with patients suffering from bulbar polio, a form of the disease that attacks the nerves controlling breathing. The state-of-the-art technology at the time was the negative pressure ventilator, famously known as the “iron lung.” This device was essentially a large metal tank that encased the patient’s body, using a vacuum to expand the chest and draw air into the lungs.
While it worked for some, the iron lung was failing patients with bulbar polio. They couldn’t protect their own airways, and mortality rates soared to a devastating 80%. Amid the crisis, an anesthesiologist named Björn Ibsen proposed a radical solution. Instead of pulling air in from the outside, what if they pushed it in from the inside?
Ibsen’s idea was to perform tracheostomies and use positive pressure ventilation (PPV), delivered manually with a simple rubber bag. It was a monumental undertaking. Medical students were recruited to sit by the bedsides, hand-ventilating patients 24 hours a day. The results were astounding. Mortality rates plummeted to around 40%. This moment was a turning point. It marked the first large-scale use of PPV for neurological injury and, in doing so, created the very first intensive care unit (ICU). The core lesson was clear: securing the airway and controlling ventilation were primary, life-saving neuroprotective interventions.
The Rise of a Dogma: The Hyperventilation Era
As positive pressure ventilators became standard in hospitals, clinicians in the 1970s made a powerful observation. When they increased the ventilator rate to “blow off” carbon dioxide, they saw a rapid and reliable drop in intracranial pressure (ICP). This made perfect physiological sense at the time. Think of the skull as a sealed container. When you induce hypocapnia (low PaCO₂), the blood vessels in the brain constrict. This reduces the total volume of blood inside the skull, making more room to accommodate swelling from a brain injury.
The effect was so consistent that prophylactic hyperventilation—intentionally keeping PaCO₂ levels very low (around 25-30 mmHg)—became the standard of care for severe traumatic brain injury (TBI) for nearly three decades. It was seen as a simple, effective, and benign tool to control dangerous intracranial hypertension. For an entire generation of doctors, it was the first-line therapy for a “tight brain.”
The Paradigm Shift: A Reckoning with Ischemia
The 1990s brought a dramatic change in thinking, fueled by new and better monitoring technology. Tools like jugular venous oxygen saturation (SjvO₂) and direct brain tissue oxygen monitoring (PbtO₂) gave clinicians a window into what was actually happening inside the brain. What they saw was alarming.
The aggressive vasoconstriction caused by hyperventilation was a double-edged sword. While it lowered ICP, it was also choking off cerebral blood flow (CBF) to critically low levels. It was like tightening a tourniquet to stop bleeding—effective, but at the cost of starving the tissue of oxygen. This self-inflicted damage, known as cerebral ischemia, was happening in the most vulnerable parts of the injured brain.
A landmark study by Muizelaar et al. in 1991 was the final nail in the coffin for routine hyperventilation. The randomized trial showed that patients with TBI who received prophylactic hyperventilation had significantly worse neurological outcomes than those who were kept at a normal PaCO₂ (normocapnia). The therapy that was supposed to be protecting the brain was, in fact, harming it.
At the same time, another concept was emerging: the “double hit.” Clinicians realized that the high tidal volumes and respiratory rates needed to achieve profound hypocapnia were causing ventilator-induced lung injury (VILI). This lung damage could lead to Acute Respiratory Distress Syndrome (ARDS), which in turn caused hypoxia and inflammation—a second “hit” to the already injured brain.
The Modern Approach: A New Balance of Power
The lessons from the hyperventilation era forced a complete re-evaluation of our goals. The pendulum swung away from aggressive intervention toward a more nuanced, balanced strategy. Today’s approach is built on a few key principles that directly evolved from our past mistakes.
1. The Primacy of Normocapnia
The modern standard is to maintain a state of normocapnia, targeting a PaCO₂ between 35 and 45 mmHg. This “Goldilocks” zone avoids the dangerous vasodilation of hypercapnia and the ischemic vasoconstriction of hypocapnia. Hyperventilation hasn’t disappeared entirely, but its role has been drastically curtailed. It is now reserved only as a temporary “bridge” therapy—a short-term rescue maneuver for a patient with signs of active brain herniation, used only while more definitive treatments like surgery or osmotic therapy are being prepared.
2. Lung Protection as Brain Protection
The “double hit” theory taught us that the lungs and brain are a team; you can’t sacrifice one for the other. We now know that preventing ARDS is a critical part of brain protection. This led to the adoption of lung-protective ventilation strategies in the neuro-ICU. This means using lower tidal volumes (around 6-8 mL/kg of predicted body weight) to prevent lung stretch and applying moderate levels of Positive End-Expiratory Pressure (PEEP) to keep the lungs open and improve oxygenation.
3. A Reassessment of PEEP
For years, PEEP was feared in the neuro-ICU. The concern was that the pressure would impede venous drainage from the head and raise ICP. While this is mechanically possible, we’ve learned that the fear was largely overstated. Studies have shown that in most patients, moderate levels of PEEP (up to 10-15 cmH₂O) have minimal impact on ICP, especially if blood pressure is supported. The benefits of using PEEP to prevent alveolar collapse and avoid hypoxia—a potent cause of brain swelling—far outweigh the risks in most cases. Stiff lungs from ARDS, it turns out, can even shield the brain from the pressure of PEEP.
4. Individualized, Monitored Care
Perhaps the biggest lesson is that there is no one-size-fits-all approach. The evolution from iron lungs to smart ventilators has been paralleled by an evolution in monitoring. Today, we can integrate data from the ventilator with advanced multimodal monitoring, including ICP, CPP, and brain tissue oxygen levels. This allows us to tailor our strategy to the individual patient, finding the optimal balance between lung and brain protection for their specific injury and physiology.
Conclusion: Learning from Our Past to Improve the Future
The history of neuro-ventilation is a powerful reminder that medicine is always evolving. The journey from the polio wards of Copenhagen to the modern neuro-ICU shows a clear progression: from basic life support to a flawed but logical intervention, and finally to a sophisticated, evidence-based practice.
As you begin your clinical rotations, remember this history. When a neurosurgeon is wary of PEEP, or an attending emphasizes strict PaCO₂ control, you’ll understand the historical context behind their reasoning. By appreciating the lessons learned from the iron lung, the hyperventilation era, and the dawn of brain-protective strategies, you are better equipped to provide safe, effective, and thoughtful care to your patients. You are not just managing a ventilator; you are continuing a legacy of learning and improvement that is at the very heart of critical care.